

SUBSCRIBE TO OUR FREE NEWSLETTER
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.
5
#000000
#FFFFFF
To donate by check, phone, or other method, see our More Ways to Give page.
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.

The administration’s agenda for the last two years is built around the concept of less access to life. It has committed billions of taxpayer dollars to this mission.
It’s such a simple idea—that our nation was founded to provide its citizens and new arrivals with more life. Our unique form of government, grounded in the notion of self-determination, explicitly seeks to expand life possibilities for more people so that they might realize gifts granted at birth. Why didn’t this occur to me sooner? After all, “life” so clearly precedes “liberty and the pursuit of happiness” in the Declaration of Independence.
To our detriment, we are now living through a period where the person we elected president, whose predecessors largely upheld the nation’s founding principles, seeks to bury its most basic intent. The administration’s agenda for the last two years is built around the concept of less access to life. It has committed billions of taxpayer dollars to this mission. When superimposed on their repetitive attempts to disempower women, people of color, and ethnic minorities, the four efforts that follow cap a prolonged assault on life:
The allocation of vast resources to expel several hundred thousand people from the country, sidestepping their due process rights. All emigrated to fulfill more of life’s possibilities in safer and more nurturing surroundings. A strong majority have bolstered the nation’s economic might and cultural richness. Read this Guardian article for a full grasp of the horrifying actions done in our name and paid for with taxpayer dollars. For those expelled, life’s possibilities have been lessened. Ours too are diminished, as their contributions are subtracted from community life.
Preserving an entitlement to more life in all its various forms inspires a cause that warrants universal backing.
The denial of science-based findings regarding climate disruption and positive health measures. This translates into many more citizens having fewer life options. On the climate front, the administration has contended that more oil enhances our lives. The truth is that more oil equals less life. Profligate burning of it disrupts the proper functioning of the atmosphere, sickens more people, and causes extreme weather that results in severe dislocations and needless deaths. At the same time, disregarding years of learning regarding preventive health measures and positive treatment protocols shrinks the chances of more of us for a full life.
The constriction of public discourse by curtailing press freedom and criminalizing constitutionally protected citizen dissent. The upshot is that the breadth and depth of the field of ideas available to us as citizens is considerably constrained. Life’s richness is fed with bursts of fresh air, not with heavy doses of government suppression. When the range of the possible is narrowed, there is less of life’s potential.
The direction of public resources in support of the fortunes of a few extremely wealthy people. This distortion shuts off opportunities for more citizens to spread their economic wings in pursuit of a better life. The so-called “American Dream” has become a mirage of unrealizable expectations for 90% of the population. Ironically, it was the throttling of these expectations that stoked the anger and resentment of a plurality of our fellow citizens and led to the election of a person committed to limiting life chances for millions.
These acts, designed to deprive constituents of more life, are evidence of a transgression more egregious than all the others this administration has perpetrated. It demands immediate attention and redress.
Strategically speaking, fighting for more life is easier to grasp than fighting for democracy, The latter asked people to stand together in defense of an abstract idea. For some it had partisan overtones. In contrast, preserving an entitlement to more life in all its various forms inspires a cause that warrants universal backing. It would be sufficient for undertaking a mass movement fueled by nonviolent direct action.
Who of us, regardless of political affiliation, would advocate for less life? This is the cause for which we must fight now—to regain the ground we have lost, and to realize even more fully the primary intent of the Declaration of Independence: more life.

“This is not normal," said the president of the union representing CDC workers. "What we are witnessing is the dismantling of public health infrastructure our country relies on."
Reporting published over the weekend detailing the "zombified" state of the preeminent public health institution in the US, the Centers for Disease Control and Prevention, sparked deep alarm among advocates and experts, who warned that President Donald Trump's gutting of the agency leaves the country badly unequipped to handle future emergencies.
"The grim state of affairs at the Trump CDC should terrify everyone," Brad Woodhouse, president of the advocacy group Protect Our Care, said in a statement on Monday in response to reporting by The New York Times, which shows how Health and Human Services Secretary Robert F. Kennedy Jr. and other administration officials have made the CDC "a skeleton of the powerhouse it was."
The Times noted that, as of May 2026, the CDC had 30% fewer employees than it did before the Trump administration initiated mass layoffs at the agency and across the federal government last year.
There is also a leadership vacuum at the agency, according to the Times, which reported that "only one of the 11 center directors from March 2025 remains at the agency" and "most of the other centers are being run by acting directors, some of whom were elevated from jobs one or two levels below." The current CDC director is Dr. Erica Schwartz, who "has made no public statements about the importance of childhood vaccines or corrected misinformation from her boss, Mr. Kennedy," the Times observed, even as recorded measles cases reach levels not seen in decades.
"Interviews with more than 30 current and former employees reveal the agency is now tightly controlled by Mr. Kennedy and his associates, and its scientists are finding it increasingly difficult to do their jobs effectively," the newspaper reported.
Dr. Demetre Daskalakis, who headed the CDC's respiratory disease center before resigning in protest last year, told the Times that the Trump CDC "is not acting like how an agency like that should act." In his resignation letter, posted to social media in August 2025, Daskalakis warned that "the nation’s health security is at risk and is in the hands of people focusing on ideological self-interest."
According to the Times, the CDC's center for emerging and zoonotic diseases, which manages Ebola and hantavirus, "now has nearly 300 fewer employees than in March 2025, and the respiratory disease center has lost nearly 200—about 17% in each case."
"RFK Jr. has gutted the office that works on dangerous, killer emerging diseases," US Sen. Chris Murphy (D-Conn.) wrote over the weekend. "Disaster in waiting."
Woodhouse of Protect Our Care said Monday that "after a catastrophic global pandemic followed by a record-breaking measles crisis, the CDC should be better prepared than ever."
"Instead, the agency keeps getting caught with its pants down thanks to Donald Trump and RFK Jr.’s self-sabotage and war on science," said Woodhouse. "Investigations are coming, but resignations should come much sooner.”
The Times reporting coincided with new data from American Federation of Government Employees (AFGE) Local 2883, which represents CDC workers. The union said the CDC has lost over 3,800 employees during Trump's second term, nearly a third of the agency's total workforce.
“This is not normal," said Yolanda Jacobs, president of AFGE Local 2883. "What we are witnessing is the dismantling of public health infrastructure our country relies on."
"CDC workers have endured eighteen months of chaos and confusion, from detrimental layoffs and RIFs, to being left in a constant state of panic about job security. This turmoil cannot continue," Jacobs added. "Our workers, who have dedicated their lives to serving the American people, deserve better. Our country deserves an agency that is fully prepared to protect the public’s health within and outside its own doors. Protecting our nation’s public health workers also protects our nation’s public health.”
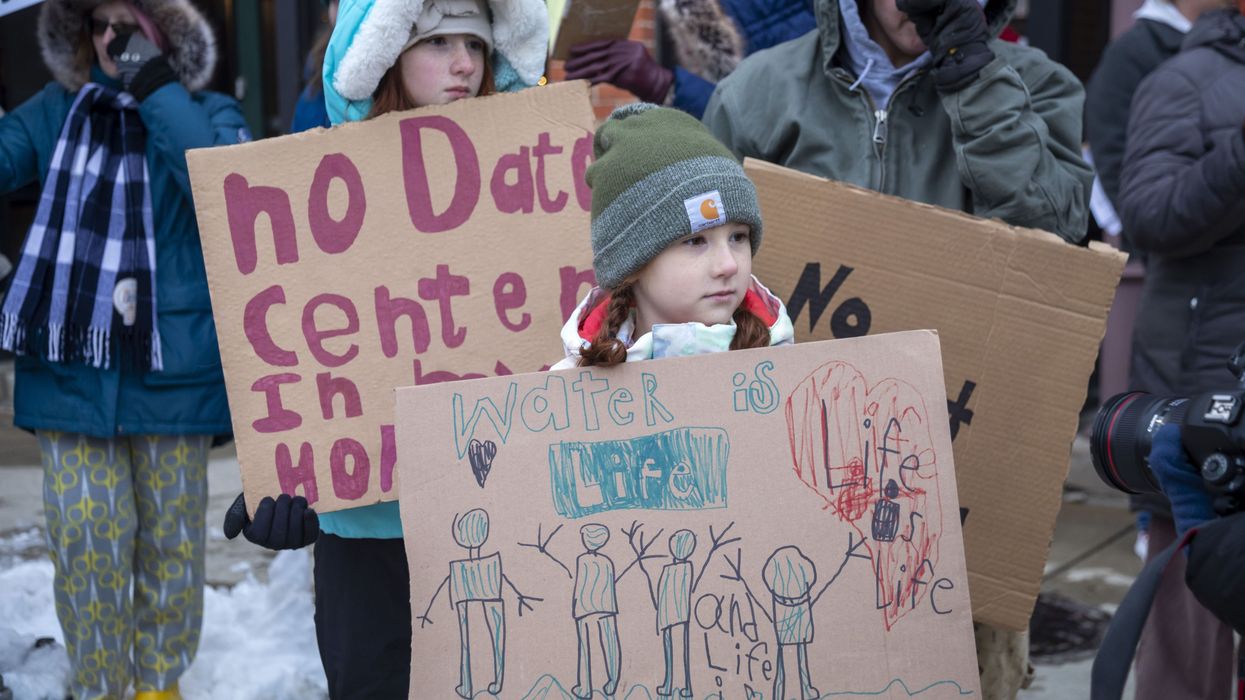
To fight back against Big Tech, the movement must articulate a clear diagnosis of the problem, adapt to changing political landscapes, translate early wins into lasting policy, and forge broad alliances.
As data centers sprout across the nation, a new movement is emerging to challenge the tech companies building them. The rapid spread of these facilities raises critical environmental, health, economic, and political questions, positioning health, climate, and social justice activists to play a central role in elevating these questions for the 2028 elections.
To date, the movement against data centers has made impressive gains. In the first four months of 2026, local opposition disrupted at least 75 data center projects worth approximately $130 billion. In June 2026, more than 200 advocacy organizations urged Congress to reject legislation fast-tracking the financing and permitting for large AI data centers. By July, New York State Gov. Kathy Hochul imposed a statewide moratorium on new hyperscale data centers—a model other states and cities are considering. National groups such as Food and Water Watch, the NAACP, Union of Concerned Scientists, and the Democratic Socialists of America have distributed resources to support local campaigns.
Public opposition has shifted dramatically alongside this activism. In August 2025, a poll of 4,000 Americans showed 43% supported having a data center built near their home. Just eight months later, in Spring 2026, support plummeted to 21%—a drop described by the pollster as “a scale of change in public opinion that I didn’t know was still possible in the US.”
However, the movement also faces significant headwinds. Big tech companies like Meta, Google, Microsoft, and Open AI are investing hundreds of billions of dollars to support new data centers to meet AI’s growing computing demands. As Karen Hao explains in Empire of AI, tech owners believe being first and largest will ensure dominance, driving relentless expansion.
Data center and AI activists are raising core questions: Who should decide whether communities allow data centers? Who pays the long-term costs and reaps the benefits?
Earlier environmental movements received some support from presidents seeking environmental legacies, but President Donald Trump provided public subsidies enabling the AI industry to bypass opponents.
Despite widespread local opposition to data centers and bipartisan support for regulation, the movement lacks a comprehensive national narrative to counteract the industry claim that AI will solve all problems. To tell such a story, previous and current movements must articulate a clear diagnosis of the problem, adapt to changing political landscapes, translate early wins into lasting policy, and forge broad alliances. My analysis of past successes of health and environmental movements suggests five strategic pathways emerge for the data center movement.
Successful movements link distinct problems to create multiple paths into activism. The women’s movement brought together advocates for sexual and reproductive healthcare, women of color, working women, lesbians, and people with disabilities. This inclusive alliance built the power needed to expand access to abortion, ban pregnancy discrimination, and protect women from insurance industry bias. Even when differences among its supporters emerged, the movement’s unifying goals provided a framework for common action.
Data center activists have raised health, environmental, and social justice concerns: increasing air pollution, water depletion, and excess noise. One study estimates that by 2028, the annual public health costs of data center air pollution will reach $20 billion. Activists also recognize that data center expansion enables AI and tech companies to deepen surveillance, target harmful social media campaigns, and facilitate harms to mental health.
Organizers can build a unified constituency by addressing both immediate harms (unregulated construction) and systemic issues (AI expansion enriching billionaires at public expense).
Effective movements united diverse groups around shared economic and social interests. The Fight for $15 movement successfully raised the minimum wage to at least $15 an hour, in at least 68 cities, counties, and states, winning more than $150 billion in higher pay for more than 26 million workers. It united low-wage workers, unions with the resources to pay organizers, and activists from Black Lives Matter and #MeToo.
Data centers activists can replicate this coalition approach. They can link residents concerned about the impact of local data centers and workers and labor unions whose jobs will be displaced by the growth of AI. They can enlist advocates for democracy, social justice, and tax reform who object to the political influence and low taxes of tech billionaires.
Movements frequently debate whether to emphasize immediate or long-term goals. In the movement for universal healthcare, organizers argued whether to support the Affordable Care Act as a step forward or to demand Medicare for All to reduce healthcare industry power.
Mark Hannay, from Metro New York Health Care for All, suggested a “both-and framework.” Metro fought for Medicare for All, but also for funding for New York City’s public hospitals and Medicaid and stronger regulation of the healthcare industry.
Data center and AI activists adopt this approach by pairing immediate demands—such as construction moratoria and stronger air and water protections—with long-term systemic reforms, including antitrust enforcement, elimination of corporate subsidies, and higher taxes on tech billionaires.
ACT UP, a leading force in the fight to get the government to respond more effectively and rapidly to the AIDS epidemic, used inside-outside, disruptive and conventional, and litigation and community organizing to achieve its goals. ACT UP found that multiple approaches increased pressure on the government to respond and mobilized more constituencies.
The data center movement has already used community organizing, demonstrations, litigation, legislation, and media campaigns to advance its goals. Maintaining this diversity, aligning its deployment to maximize impact, and developing a strategic plan for 2028 and beyond will help sustain momentum and drive policy wins.
Enduring movements unite people around a vision grounded in shared values. Martin Luther King Jr.’s vision of a world where character triumphed over skin color provide a moral vision for the civil rights movement. For more than a decade, environmental justice activists have proposed that all people have the right to environmental protections and a voice in shaping their communities’ environments. This expansive vision has enabled this movement to win local, state, and national policy changes and bring together environmental, climate, people of color, and women’s activists across the country.
Data center and AI activists are raising core questions: Who should decide whether communities allow data centers? Who pays the long-term costs and reaps the benefits? What role should voters—rather than tech industry executives—have in directing the future of AI?
By offering clear, practical answers and using the experiences of past activist campaigns, the growing data center-AI movement can put these questions on the nation’s electoral and political agenda. In doing so, they can become a powerful force for healthier, safer, and more just communities and a world where AI is used to benefit humanity.
The Environmental Protection Network listed actions "that could increase pollution-related health risks, weaken protections that would otherwise reduce those risks, or shift more costs onto families and communities."
As President Donald Trump claims that US communities fighting against artificial intelligence data centers are promoting "poverty, crime, and squalor," a Thursday report details how his administration "is weakening or proposing to weaken pollution and permitting safeguards" for such facilities, to the detriment of public health.
The Environmental Protection Agency's "mission is to protect human health and the environment," notes the new report. "Yet Administrator Lee Zeldin has made turning the United States into the 'AI capital of the world' a pillar of EPA's work."
"The Hidden Health Costs of AI Data Centers"—from the Environmental Protection Network (EPN), which is made up of hundreds of former EPA staffers—documents "at least 30 federal actions since January 2025 that could increase pollution-related health risks, weaken protections that would otherwise reduce those risks, or shift more costs onto families and communities."
As the document details: "17 of the 30 explicitly cite or target AI or data centers in the action itself or in an agency statement specifically describing or justifying that action. The remaining 13 affect how data centers are powered, what pollution safeguards apply, how projects are approved, or how federal requirements are enforced."
The report points to the EPA policy that "made it easier for some long-idled facilities to restart without triggering the major air-permitting requirements," as well as its proposed elimination of federal carbon pollution standards for fossil-fueled power plants and some outstanding state clean-air requirements for areas that failed to meet ozone standards.
The publication also notes the EPA's extended deadlines for several coal-plant wastewater requirements, newly regulated coal-ash units, the 2024 oil and gas standards, and for states to submit plans to reduce visibility-impairing pollution. The agency further interpreted a policy on nonemergency backup generator use that it framed as a move supporting AI and data centers.
It's not just the EPA. The US Department of Energy "authorized grid use of backup generation at data centers and other major facilities during emergencies," the report explains, while the Army Corps of Engineers "expressly named data centers as examples of commercial development covered by" a streamlined water permit.
The race for AI data center growth shouldn’t mean weaker safeguards on pollution. Former EPA official Walter Mugdan explains why strong enforcement matters when families’ health is at risk.What’s being weakened? Read the full report at the link in the comments.
[image or embed]
— Environmental Protection Network (@enviroprotnet.bsky.social) September 10, 2026 at 4:39 PM
"No study has yet calculated the combined health effects of these actions, but the direction is clear," the report says. It cites a study from this year that estimates air pollution related to data centers "could impose roughly $11.7 billion to $20.9 billion in annual public health costs by 2028," and "contribute to roughly 600,000 asthma symptom cases and 1,300 premature deaths."
Dan Costa, who spent about 35 years at EPA studying the impact of air pollution on human health and led its national research program on air quality, climate, and energy, said that "the existing health study gives us a picture of the potential health burden under particular data-center growth and emissions scenarios."
"But it does not estimate the additional health effects of the 30 federal policy actions EPN documents," he stressed. "That is the analysis EPA should be doing now: Measuring what these sources actually emit, modeling both local and regional air-quality effects, and translating those changes into health impacts."
In addition to laying out the Trump policies and their risks, the publication highlights how his agenda on AI data centers conflicts with voters' wishes. An April poll conducted by YouGov for EPN found that:
"You would think a build-out of this magnitude would mean more vigilance from EPA: stronger safeguards to make sure companies control their pollution, more science to understand what this scale will bring, and more monitoring," said Dr. Lynn Goldman, a pediatrician and former EPA assistant administrator. "Instead, EPA and other federal agencies are doing the opposite."
The EPN report was published amid mounting calls for Congress to rein in artificial intelligence development in the wake of Jacob Coxon, a researcher at Anthropic who previously worked at OpenAI, quitting, and spotlighting fears within the industry that the rapidly advancing technology "could kill us all by the end of the decade."
Sen. Bernie Sanders (I-Vt.) and Rep. Greg Casar (D-Texas) have introduced legislation that would permanently ban the development of "superintelligent" AI until a federal body is created to regulate it—and, according to polling results published on Wednesday by Data for Progress, 68% of likely voters in the United States support that proposal.
Sanders has also partnered with Rep. Alexandria Ocasio-Cortez, (D-NY) for the Artificial Intelligence Data Center Moratorium Act, which would pause construction on the facilities "until strong national safeguards are in place to protect workers, consumers, and communities, defend privacy and civil rights, and ensure these technologies do not harm our environment."

"The most serious risk is premature death," said one physician.
A senior Iranian health official on Tuesday accused the United States of deliberately targeting Iran's medical infrastructure amid a worsening shortage of critical medicines as President Donald Trump's illegal US-Israeli war of choice against Iran drags on.
Iran's pharmaceutical system is straining under US bombing, blockade, and sanctions that have severely disrupted trade and transportation in the Middle East nation of around 90 million people. Iranian officials say shortages of roughly 800 medicines—including dozens of essential drugs—are affecting the treatment of cancer and other serious illnesses.
“The enemy has identified medicine as one of the sensitive areas of the country, and is trying to denigrate and portray Iran’s conditions as unfavorable by releasing content in the press and social media," Deputy Health Minister Mahdi Pirsalehi, who also heads Iran's Food and Drug Administration, told Al Jazeera.
Pirsalehi has said that more than 50 factories and pharmacies have been damaged or destroyed by US and Israeli bombing during the six-month war. The attacks have exacerbated existing shortages.
One gastroenterologist and university professor in Tehran, who spoke to Al Jazeera on condition of anonymity, sounded the alarm on what she called a "staggering" rise in drug prices—including for domestically produced generic medications—caused in significant part by the US naval blockade.
“Reports that rotavirus vaccine imports have been halted because of the maritime blockade—and that influenza vaccines may soon face the same problem—represent a serious and alarming threat to nationwide efforts to prevent vaccine-preventable communicable diseases,” she said.
“Runaway inflation, poverty, and inadequate access to essential food groups among vulnerable populations, including infants, children, and pregnant women, signal the onset and spread of malnutrition,” she added, warning of the risk “of both communicable and noncommunicable diseases, creating a vicious cycle in which malnutrition develops and progressively worsens."
For ordinary Iranians, empty pharmacy shelves, delayed treatments, and prohibitively expensive prescription drugs have become the new normal.
One Iranian pharmaceutical company recently announced price increases for scores of drugs, including a 543% rise in the price of the Alzheimer's medication donepezil, a 308% higher cost for the antibiotic clarithromycin, and a 135% spike in acetaminophen and diphenhydramine syrups, according to reporting by Tasnim News Agency.
Dr. Hassan Nayeb Hashem told Deutsche Welle last month that "for many specific diseases, there is effectively no substitute" for prescribed drugs.
"If the medicine becomes inaccessible, patients can develop complications much sooner," he said. "The most serious risk is premature death."
One patient requiring testing for an abdominal and pelvic mass recently told Iran International that CT and MRI scans now cost over $100, even with Social Security insurance—the equivalent of a month's pay for many Iranians.
“How are we supposed to pay these costs with such meager incomes?” they asked.
A 33-year-old man said the exorbitant cost of dental treatment has left him without half of his teeth.
“I feel like I’m 60,” he said. “The bitter part is that this humiliating way of life has become normal for me.”
Another Iranian said they feared what would happen if anyone in their family got sick this winter.
“We’re stressed about where we would get the money for treatment," they said, "if God forbid we or our children even catch a cold."

"This proposal declares open season on the nation's waterways," one critic charged.
President Donald Trump's administration sparked fresh fury on Friday when it proposed a supplemental rule to further gut Clean Water Act protections for streams and wetlands in the wake of a "catastrophic" US Supreme Court ruling three years ago.
The supplemental proposal from the Department of the Army and Environmental Protection Agency builds on their widely criticized proposed rule from November for defining "waters of the United States" (WOTUS)—both of which go further than the high court did with its 2023 decision in Sackett v. EPA.
While the American Petroleum Institute and some Republicans in Congress joined Assistant Secretary of the Army for Civil Works Adam Telle and EPA Administrator Lee Zeldin in promoting the new proposal, environmental and public health advocates sounded the alarm.
"What the Supreme Court did in its Sackett decision was an inexcusable assault on clean water," Jon Devine, director of freshwater ecosystems at the Natural Resources Defense Council, said in a Friday statement. "Communities and wildlife will pay the price until Congress fixes it. The Trump administration's answer has been to make a bad situation worse."
"This proposal declares open season on the nation's waterways. It denies federal protection to virtually all wetlands and more than three-quarters of our streams, endangering drinking water supplies and flood-prone communities—and the agencies admit it themselves," he noted. "The proposal would virtually eliminate protection for freshwater wetlands. Their own analysis says most streams would lose protection, with the West hit hardest."
Food & Water Watch legal director Tarah Heinzen declared that "Trump is taking yet another sledgehammer to our bedrock Clean Water Act, shamelessly doubling down on his initial terrible proposal to strip protections from countless streams and wetlands."
"Make no mistake: This unlawful proposal gives bad actors the green light to fill, drain, and poison sensitive waterways from coast to coast," she warned. "The result will be dirtier water for everyone. The administration must reverse course on this dangerous proposal."
Gary Belan, senior director of American Rivers' Clean Water Program, stressed that "our nation's water resources are precious and increasingly at risk. This is not the moment to be jeopardizing the nation's water security by narrowing the safeguards of the Clean Water Act."
The public comment period for the initial proposal has closed but, as Belan noted, the publication of the supplemental rule in the Federal Register kicks off a new 30-day period. He said that "while we appreciate EPA's effort to seek more public comment, the proposed changes will have consequences that will impact communities across the nation if finalized."
"The proposed definitions do not reflect the established science on how rivers function and would significantly reduce the scope of the Clean Water Act," he continued. "When headwater and intermittent streams and wetlands lose protection, downstream flooding worsens, the costs of drinking water treatment rises, and water supplies become less reliable."
Jim Murphy, the National Wildlife Federation’s associate vice president for legal advocacy, pointed out that "this is now the fifth effort to define the scope of the waters protected by the Clean Water Act in the past decade. We need Congress' help to get off this merry-go-round at a place that protects our waters, our wildlife, and our way of life."
"The administration is clearly struggling to craft a rule that will hold up in court while satisfying their donors' desire to effectively scrap these protections wherever possible," he added. "One thing is clear: If we don’t protect our streams and wetlands, the cost of dirtier drinking water and increased flooding will flow downstream to households at a time when most Americans are living paycheck to paycheck."
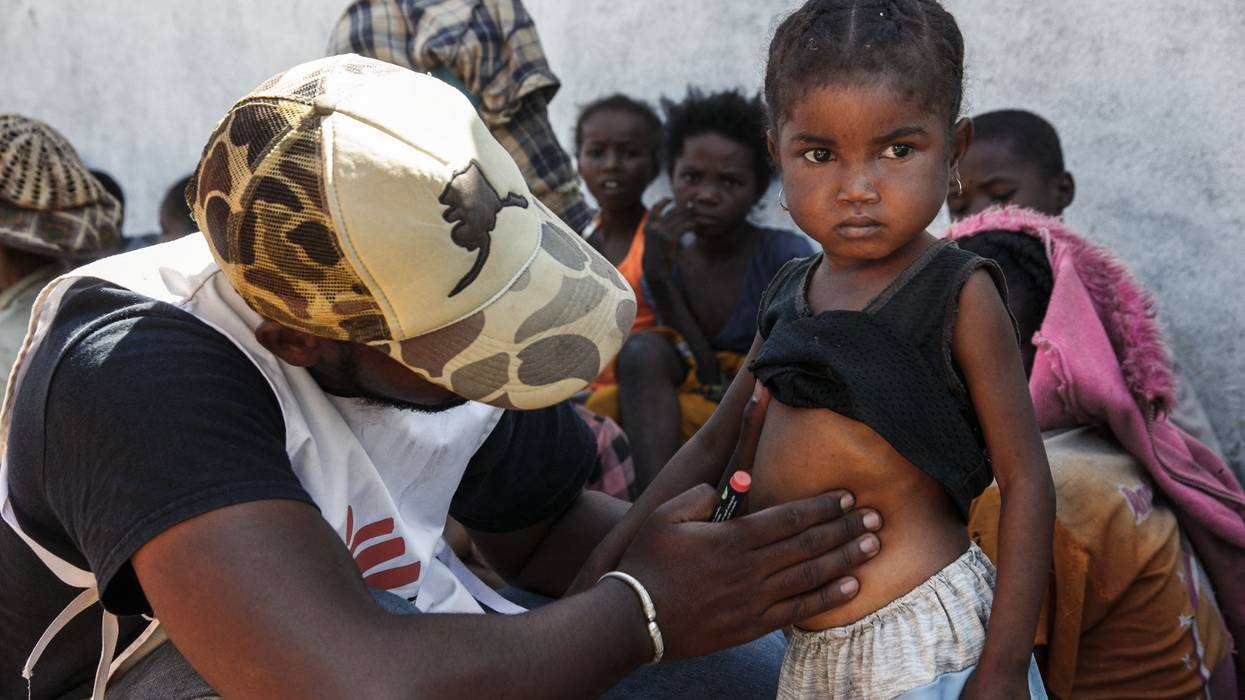
"It will be patients who will pay the ultimate price," said one global health advocate.
The US Congress has pushed back against President Donald Trump's efforts to slash foreign aid, which has long been supported by Democrats and Republicans alike—but a new report on more than a dozen Memoranda of Understanding that the White House has reached with countries that have long relied heavily on healthcare assistance shows that the administration is underspending "congressionally appropriated global health funds by potentially billions of dollars," as it pushes its "America First Global Health Strategy."
That's according to Public Citizen, which on Sunday joined Partners In Health in releasing an analysis of documents that the two nonprofits obtained after suing the Trump administration and filing a Freedom of Information Act (FOIA) request.
The groups reviewed the MOUs that have been signed for 18 out of 34 countries whose agreements have been negotiated by the US State Department, including Rwanda, Liberia, Burundi, and Madagascar.
Although Congress has voted to keep foreign aid levels relatively constant—rejecting a budget that called to slash global health spending by $6.2 billion before approving one that proposed a $615 million decrease in spending—the report finds that the MOUs cut foreign health aid by about $2 billion by 2030, compared to 2024 levels.
“These documents suggest that the Trump administration is on course to underspend on global health by billions of dollars compared to what Congress has ordered, risking lives and allowing diseases to spread,” said Peter Maybarduk, director of the Access to Medicines program at Public Citizen. “The administration must answer how and when it intends to invest the missing billions for health.”
Overall, funding for programs that aim to prevent the spread of diseases including HIV/AIDS, tuberculosis, and Ebola—which is currently spreading in the Democratic Republic of Congo's fastest-spreading outbreak on record—is set to be reduced by 59% from historical spending, according to the MOUs viewed by Public Citizen and Partners in Health.
Some countries would see their health assistance from the US plummet even more, with Rwanda's MOU stipulating a 97% reduction in US health aid. Liberia is set to receive 84% less funding for health initiatives by 2030, and Burundi is set to lose 78% of its aid.
"Partners In Health provides direct care in Rwanda, Liberia, and Sierra Leone, along with seven other countries, and expects under-spending of these funds to impact patients’ access to care," said Public Citizen.
The MOUs also demand that the countries meet strict co-financing requirements to make up for their lost funding, and governments in poor countries across Africa could face penalties "which could worsen funding cuts" if they miss the co-financing targets.
"The planned decreases in US funding are larger for several countries than the funding increases from partner governments," reads the report. "For more than half of countries (11 out of 18), co-financing commitments fall short of the US government’s cuts over five years compared to baseline US government funding."
Countries are likely to struggle to meet the co-financing requirements in the MOUs, warned Public Citizen and Partners In Health.
Malawi would be required to secure new healthcare funding equal to 56% of the country's total health expenditure, the report found. With Uganda also facing co-financing requirements from international health organizations including the Global Fund and Gavi, the East African country would be required to mobilize funds equal to 44% of its total health budget.
"These funding cuts will cause death and disease that is preventable,” said Vincent Lin, associate director of health policy and advocacy for Partners In Health. “The State Department is setting up other countries for failure with the co-financing requirements outlined in these agreements, but it will be patients who will pay the ultimate price.”
Maybarduk told The Washington Post that Sierra Leone will be required under its MOU to fill a 71% health funding gap by 2030.
“It’s going to be very difficult, and if a country like that falls behind, and then is punished for that, then of course the health problems compound," said Maybarduk.
The State Department denied to the Post that the Trump administration will not spend all the foreign health assistance funds appropriated by Congress; it suggested that more of the money than usual may go to religious organizations as well as an "innovation fund" to support US technology that aims to fight disease.
Last week, Public Citizen sued the Trump administration under FOIA to obtain the rest of the MOUs that remain hidden from the public.
The White House, said the group, "has kept the public in the dark about the full details of its plans for the future of US support for global health."
"The State Department has negotiated these bilateral agreements," the group said, "on rushed timelines with limited participation from civil society and affected communities."
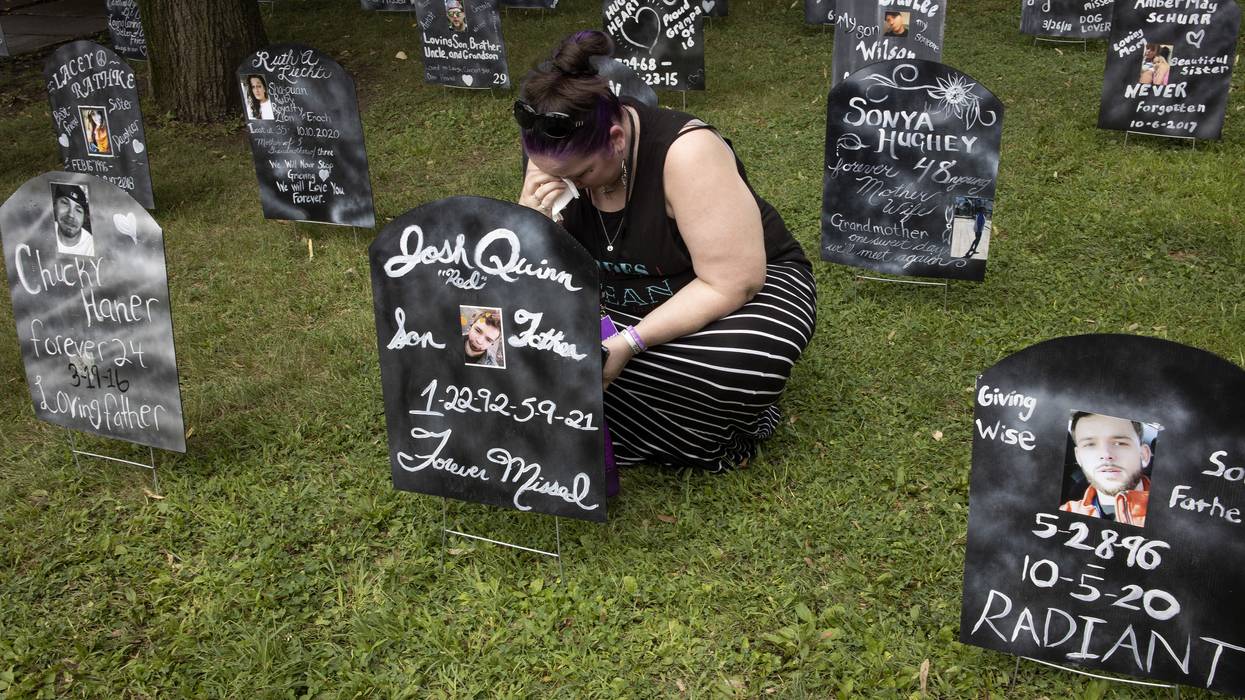
This money was won because communities suffered extraordinary harm and hundreds of thousands of people lost their lives, so funds should build and expand capacity of much-needed health infrastructure and create lasting systems of care.
Nearly $58 billion is now flowing into states and local governments after the recent settlement with Purdue Pharma and other companies whose actions fueled the overdose epidemic, one of the deadliest public health crises in American history. For the first time in a generation, local communities have a critical opportunity to decide how this money is spent and allocate funding to build systems on their own terms, systems that actually save lives and provide care rooted in dignity.
The question is whether state, county, and municipal officials will actually take that chance.
The settlement money belongs to the people that paid the price. It is restitution for those lives lost, for families devastated, and for communities harmed not only by addiction and overdose, but by decades of failed punitive policies that criminalized suffering instead of treating it. It doesn’t belong to politicians, hospital systems, police departments, or consultants.
That means people directly impacted by overdose, addiction, incarceration, homelessness, and family separation should help decide how these dollars are spent. Too often, they are shut out of that decision entirely. In many states, opioid settlement decisions are made in private meetings with little public awareness, minimal reporting requirements, and limited opportunities for ordinary residents to participate. Some local governments still have no meaningful public process at all.
As federal health and social service funding faces growing cuts, many states and localities are quietly eyeing opioid settlement dollars to backfill budget gaps or prop up systems that should already be publicly funded.
When people get involved, the results improve. More states are passing legislation requiring reports on opioid settlement spending. In Hancock County, Maine, there was initially no public framework for opioid settlement spending. After a local advocate stepped forward to engage county officials, authorities created a committee of community stakeholders, including people with firsthand lived experience, to help advise how to spend those funds. In Buffalo, New York, public scrutiny and press attention around the use of settlement spending on things like police equipment and snowblowers pushed local leaders toward better investments, such as recovery coaches and treatment clinic upgrades, in later funding rounds. We can see how public engagement changes outcomes.
New Jersey committed nearly $119 million to expand harm reduction centers offering naloxone distribution, syringe access, mobile outreach, and connections to care. Kentucky continues to invest in a network of legal aid providers helping people impacted by drug use expunge their criminal records. Portland, Maine spreads its opioid funds across three efforts: a needle buyback program that removes used syringes from public spaces; a housing first program that gets people into stable housing without requiring sobriety first; and contingency management, which rewards people with incentives like gift cards for staying off stimulants such as meth and cocaine.
We also know what does not work. Nevertheless, across the country, settlement dollars are still being spent on police equipment, surveillance technology, jail expansions, and outmoded treatment programs that forbid modern medications, and ineffective "just say no" style prevention campaigns. Some jurisdictions have purchased drones, tasers, license plate readers, police dogs, and narcotics detection equipment using funds that were supposed to heal communities harmed by overdose.
The most insidious trend may be one the public cannot easily see: supplantation. According to best practice guidance from Johns Hopkins University and endorsed by more than 60 organizations including my own, supplantation advises that opioid settlement funds must not replace existing funding sources. But as federal health and social service funding faces growing cuts, many states and localities are quietly eyeing opioid settlement dollars to backfill budget gaps or prop up systems that should already be publicly funded. Settlement dollars should not replace Medicaid; they should not compensate for cuts to public health infrastructure. They were never meant to become a government slush fund.
This money was won because communities suffered extraordinary harm and hundreds of thousands of people lost their lives. Funds should build and expand capacity of much-needed health infrastructure and create lasting systems of care, not patch holes created by shifting political priorities. It’s not that settlement funds should never stabilize existing programs; in some cases, communities may need to use these dollars temporarily to sustain lifesaving services that would otherwise disappear. But those decisions must happen transparently, with public input, and with a clear understanding of the trade-offs involved. Advocates have issued guidelines that can help jurisdictions think through these challenging decisions.
There is reason for cautious optimism. Advocates, impacted families, and community organizations across the country are building models for transparency, accountability, and evidence-based investment. A new National Roadmap for Spending Opioid Settlement Funds can help communities understand their local processes and push for smarter spending. It also documents problematic and promising spending across the country. Advocates in Maine, New York, and New Jersey have created websites to help community members get involved in directing opioid settlement funds. The Maine Recovery Action Project has created a national toolkit that anyone can use to start organizing residents to have a say in spending decisions.
Residents should ask simple but critical questions, such as: Where is the money going? Who benefits? What evidence supports these investments? Who was consulted?
The overdose crisis was perpetrated by decisions, made over the course of decades, that never faced accountability. We cannot afford to repeat that mistake now with resources made available to repair the damage.

Under pressure to expand nuclear energy production, the commission has proposed weakening standards protecting workers and communities from radiation exposure.
The Nuclear Regulatory Commission, or NRC, whose mission is to protect public health and safety regarding nuclear energy, has now transformed into an agency, as so many have under the current administration, to support the nuclear industry and its billionaire backers. Following other captured federal agencies like the Department of Energy, which is variably led by individuals from the very industries it is intended to regulate, the NRC is under pressure from the president to facilitate the quadrupling of nuclear energy production by 2050. This is to be accomplished by fast-tracking the licensure and building of reactors while discarding the nuclear radiation exposure safety measures in place for decades as these are seen to be onerous and financially burdensome to the industry.
The current safety standard for nuclear exposure comes from the BEIR VII (Biologic Effects of Ionizing Radiation) study. This was produced by the National Academies of Sciences, Engineering, and Medicine and concluded that there is no safe level of ionizing radiation exposure above background, noting that any excess exposure above background increases the risk to human health of cancer, and other diseases associated with nuclear exposure. This is the so-called Linear No Threshold, LNT, theory. This theory is the basis for the core precautionary safety principle and risk management approach used in the fields of ionizing radiation exposure from medicine and dentistry to nuclear energy referred to as “ALARA,” or "As Low As Reasonably Achievable.”
The problem that exists, even with current standards of radiation exposure allowance, is that they are based on the “Reference Man,” which is a 25-to-30-year-old 70 kilogram man. This androcentric standard totally disregards the fact that the majority of humanity is not represented by this standard, and that children, females, pregnant women, and the elderly are more sensitive to radioactivity exposure. In addition workers involved throughout the entire nuclear cycle are at increased risk from exposure. Furthermore, a recent Harvard study demonstrated increased cancer rates in the communities surrounding nuclear power plants within ~18.5 miles.
The current NRC proposal plans to do away with ALARA while purportedly supporting the LNT. This flies in the face of reason and is duplicitous as LNT is the basis of ALARA. Their plan is to substitute an unproven “graded approach” allowing workers to be exposed to near the regulatory limits and then taking added measures so as not to exceed it. They propose allowing the exceeding of exposure limits under “certain circumstances” setting up a banking system from subsequent year allowances amortizing over five years. They have even invoked the controversial unproven hypothesis of “Radiation Hormesis,” which proposes that a small amount of radiation causing cellular damage will stimulate cellular repair, as though to say what does not kill you, is good for you. Remember LNT.
The current proposal does just the opposite unless we stop it from moving forward. The NRC is providing a limited public comment period on this proposal which ends at midnight on August 31.
Furthermore, when implemented, these new regulations will most likely be used to reduce the already weak cleanup standards, further increasing the health risks to impacted communities contaminated from our nuclear legacy and history. These include communities such as the South Carolina Savannah River Site and New Mexico Los Alamos Nuclear Lab and Trinity Test Site to the Navajo Nation mining sites, Hanford Washington site, Nevada Test Site, St Louis Cold Water Creek, Parks Township (Pennsylvani), Rocky Flats Site near Denver, and the Santa Susana Field Lab near Los Angeles, among others.
The rationale for this current proposal is to facilitate the fast-tracking of nuclear power for the uncontrolled growth of data centers (with 1,500 new data centers currently in development), artificial intelligence, additional large commercial nuclear power plants, and new plutonium pits that are the nuclear trigger of nuclear weapons, reminding us that nuclear power remains the cover story for nuclear weapons.
The potential health risks of cancer, heart disease, birth defects, cognitive defects, thyroid and endocrine disorders, genetic mutations, and infertility are all related to ionizing radiation exposure. These are risks lasting for generations, passed on from one generation to the next. Yet, these health effects do not have to be and can be prevented if we demand the strengthening of current radiation exposure guidelines. The current proposal does just the opposite unless we stop it from moving forward. The NRC is providing a limited public comment period on this proposal which ends at midnight on August 31. Your comment is critical and can be submitted at federalregister.gov. More information can be found at www.protectbetter.org.
The Centers for Medicare and Medicaid Services' implementation of the One Big Beautiful Bill narrows the very protections Congress included to prevent vulnerable people nationwide from losing the health coverage they need.
The biggest Medicaid fight today isn't happening in Congress—it's happening inside the Centers for Medicare and Medicaid Services.
Now, a year after H.R. 1’s passage (the 2025 federal reconciliation bill enacting significant cuts and changes to Medicaid), CMS’ recently issued interim final rule (IFR) implementing the law’s work-reporting requirements in the program narrows the very protections Congress included to prevent vulnerable people nationwide from losing the health coverage they need.
The Congressional Budget Office previously estimated that more than 5 million people will lose Medicaid coverage because of these requirements. Already a conservative estimate as other organizations estimated over 10 million people are at risk of losing coverage, the number will surely be higher given CMS' IFR goes beyond the statutory language of the law.
The clearest example of this is the IFR's treatment of the medically frail exemption.
If the goal is really healthier communities and greater workforce participation, making it harder for medically vulnerable people to keep their health insurance is exactly the wrong approach.
Congress recognized that people living with complex medical conditions, disabilities, and chronic illnesses, including substance use disorder (SUD), should be protected from burdensome work-reporting requirements. As such, H.R. 1 specifically includes “medically frail” individuals among those exempt from the new requirements.
Yet CMS has added a new hurdle, putting millions of eligible Americans at dire risk of losing access to essential healthcare.
Under the IFR, people with SUD and other qualifying health conditions must also demonstrate that their condition "significantly impairs" their ability to satisfy the requirement before they can qualify for the exemption. This additional standard does not appear in the statute and will inevitably reduce the number of people who can secure the exemption.
For people living with SUD, the consequences could be profound.
While SUD is a chronic but treatable medical condition, pervasive stigma and discriminatory barriers have led to fewer than 1 in 5 people who need treatment actually receiving it. Amid persistent addiction and overdose crises, we should be making it easier for people to access the services and supports they need to become and stay well, not erecting additional barriers to lifesaving care.
Moreover, while CMS' rule relies heavily on Medicaid claims data and provider documentation to identify individuals who qualify as medically frail, the administration’s approach overlooks the reality that many people with SUD have never entered treatment due to the above-mentioned stigma and discrimination. Requiring additional documentation will not "motivate" people to seek care, as CMS suggests. Instead, it creates yet another barrier for people who are already among the hardest to reach.
When people are deprived of Medicaid access, their ability to engage in preventive care, behavioral health services, medications, and treatment that keep chronic conditions under control is also lost. And it doesn’t take a rocket scientist to understand how untreated health conditions can not just impede a person’s capacity to work but quickly lead to costly emergency services.
These are not only personal tragedies—they are costly public policy failures.
Taking away health coverage does not eliminate health needs. It just shifts and raises costs while undermining public health and safety. Access to healthcare is precisely what enables many people to work, care for their families, and be productive community members, so why are we erecting so many barriers?
If the goal is really healthier communities and greater workforce participation, making it harder for medically vulnerable people to keep their health insurance is exactly the wrong approach.
Last month, both our organizations, along with many other leading advocates nationwide, explicitly articulated these concerns and submitted comments urging the agency to reverse course and faithfully reinforce the protections Congress included in the law. While CMS' public comment period on the IFR is now closed, all those who share the same perspective can still take action by calling their members of Congress to share their concerns about the impact of H.R. 1 and specifically, how the administration is planning to implement the law.
A year after H.R. 1’s passage, the question is no longer simply about what Congress enacted—it is whether the regulations that make the law real will preserve purposeful protections or quietly erode them through administrative action.